Quick View
Loading...


Generic Peptides
Estimated Delivery: 12-26 Days (International), 3-6 Days (United States)
Return within 45 Days of purchase. Duties & taxes are non-refundable.
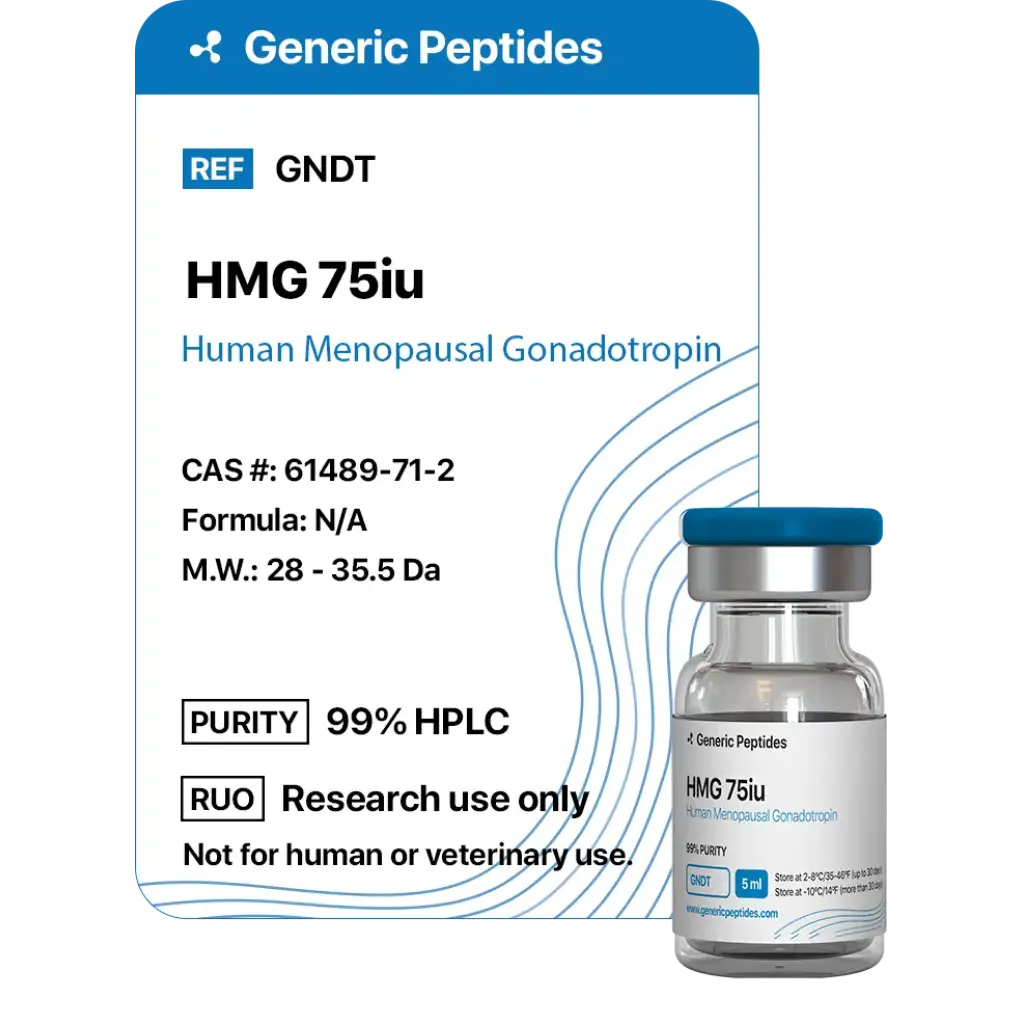
Buy HMG 75 IU by Generic Peptides at XSteroids. The abbreviation HMG expands to human menopausal gonadotropin, menotropin for short: one preparation carrying the activity of both follicle-stimulating hormone and luteinizing hormone. Generic Peptides supplies it as a single 75 IU lyophilized vial. This page covers what menotropin contains, how it is used in fertility and recovery settings, how a 75 IU vial is mixed and the anti-doping rule that names it directly.
Menotropin is a prescription gonadotropin, and the vial on this page is a research format rather than a registered medicine. The notes below are educational and are not a treatment recommendation.
Menotropin arrives in one glass vial of white lyophilized powder, standardised to 75 IU. International units are used instead of milligrams because menotropin is standardised by biological assay rather than by weight. Diluent is not supplied with the vial and has to be obtained separately; the powder is mixed before laboratory work begins.
Production begins with urine collected from postmenopausal women, and the classic vial carries 75 IU of LH activity alongside 75 IU of FSH, which is exactly what the name points to. Decades of medical use stand behind it, mostly for inducing ovulation. Recombinant products now dominate clinical practice because they offer pure FSH or pure LH free of the additional proteins that come with urinary processing, yet the urinary preparation is still the reference form.
The substance is supplied in a research format. Menotropin is an approved prescription medicine in fertility care, yet this lyophilized vial is a different article: no patient leaflet, no approved indication and no validated shelf life come with it. Generic Peptides states the 75 IU figure, while a filler list and an independent potency result remain unpublished.
Inside the testes the FSH activity targets the Sertoli cells that support sperm production, and the LH activity works on the Leydig cells responsible for testosterone. Both are glycoprotein hormones that bind their own receptors on the target cells and signal through cyclic AMP. Having both signals in a single vial is the reason HMG is described as working on the fertility side rather than only the hormone side.
HCG 5000 IU stands in for luteinizing hormone and prompts the Leydig cells to make testosterone, while sperm output is untouched by it. HMG adds the FSH signal the testes need for spermatogenesis. That is why the two are often discussed together: HCG covers the testosterone output, HMG covers fertility support.
Because it is cleared relatively quickly, menotropin is given daily or several times a week in medical use, not once weekly. Fertility protocols run for around ten days with monitoring so the dose can be adjusted, which reflects both the short action and the need for careful control of ovarian response.
The human evidence for menotropin comes from fertility medicine. In women it is used to induce ovulation, and in men with hypogonadism it is used to stimulate sperm production, often alongside HCG. The relevant markers are not visible in the mirror: sperm count and motility on a semen analysis, and testosterone, LH and FSH on blood work. Those markers move over weeks to months, not days, and the response depends on the cause of the problem, so menotropin is not a guaranteed fix for a suppressed axis.
In recreational recovery use there is no controlled trial that measures outcomes on a research vial, and no published schedule built around a 75 IU pack. Anyone treating a gonadotropin as a routine post-cycle tool is relying on user reports rather than study data, and the honest position is that blood work, not guesswork, tells you whether the axis has restarted.
Menotropin is measured in international units because it is standardised by biological assay. A single 75 IU vial is the classic research pack, and there is no approved single-vial dose for a research format, so any figure here refers to the medicine rather than to this vial.
Add 1 ml of bacteriostatic water to the 75 IU vial and the concentration is 75 IU per ml: the 10 unit mark on a U-100 insulin syringe then holds 7.5 IU, and the 20 unit mark holds 15 IU. With 1.5 ml the strength drops to 50 IU per ml, so those same 10 units hold 5 IU. Run the water down the wall and rotate gently; a glycoprotein should never be shaken, since foaming can damage it.
Approved products are designed to be used soon after mixing. No shelf life has been validated for a research vial, so refrigeration at 2 to 8 C with the solution used inside about four weeks is the sensible limit. The mixed solution should not be frozen.
HMG is read about in two contexts: fertility treatment, and the end of a suppressive cycle where the goal is to support testicular function. The honest limits are worth stating. Menotropin is a gonadotropin, not an anabolic steroid, and it does not switch the hormonal axis back on by itself. Related gonadotropin research uses Kisspeptin-10, which acts upstream at the hypothalamic level by driving GnRH. Growth hormone support is usually handled with Ipamorelin 5 mg or Sermorelin 5 mg, and Somatropin 100 IU is the direct hormone option. Repair and recovery research often adds BPC-157 5 mg or Epitalon 10 mg. None of these combinations has been formally tested with menotropin.
HMG is not a replacement for post-cycle therapy. It supplies the FSH and LH activity that the testes need, and it is discussed alongside a structured recovery plan rather than instead of one. Blood work, not guesswork, is what tells you whether the axis has restarted: testosterone, LH, FSH and sperm analysis belong in that picture. This catalog sells research peptides only, so no clinic drugs are listed here, and anyone running a hormonal cycle belongs under medical supervision.
In fertility use, the label warns about ovarian hyperstimulation, cyst rupture, multiple births and thromboembolism in women, which is why treatment happens under specialist supervision. In men, the more common effects are injection site reactions, water retention, acne and mood changes, and gynecomastia can follow if estrogen rises unchecked.
WADA lists menotropin in class S2.2.1, the testosterone stimulating peptides in males, alongside HCG and LH. Men are the only group covered, and the rule operates at all times, out of competition included. No accidental finding argument is available here, so the clause has to be treated as absolute by athletes.
Do not use the product without a diagnosed reason. Because menotropin is a urinary extract, there is a theoretical concern about infectious agents from donors, though the literature treats that risk as essentially theoretical. This page is research context and not medical advice.
Keep the lyophilized vial at 2 to 8 C, protected from light; for longer storage the freezer is the safer place. Once reconstituted, the solution belongs in the fridge at 2 to 8 C and should be used within about 28 days. Do not freeze it, and do not use a solution that has become cloudy or clumped.
HMG from Generic Peptides reaches you as the labelled 75 IU menotropin vial described in the pack listing on this page. The checkout is secure, US domestic orders take 3 to 6 days and international ones 12 to 26 days. Menotropin is also a licensed medicine, so the page separates figures that come from approved labels from those that belong to the research vial you are ordering.
It holds menotropin, also called human menopausal gonadotropin, a urinary extract that carries both follicle-stimulating hormone and luteinizing hormone activity. In the classic form a vial is standardised to about 75 IU of FSH activity and 75 IU of LH activity, which is why dosing is written in international units rather than milligrams.
Both exist. Menotropin is an approved prescription gonadotropin used in fertility treatment under the trade name Repronex and similar products. The Generic Peptides vial contains the same substance but is a lyophilized research format, with no approved patient leaflet, no approved indication and no validated shelf life.
Because they cover different cells. HCG mimics luteinizing hormone and drives testosterone production from the Leydig cells but does not support sperm production. HMG adds the FSH signal that acts on the Sertoli cells responsible for spermatogenesis. Together they cover the hormone and the fertility side of recovery.
It depends on the strength you want. With 1 ml of bacteriostatic water the vial gives 75 IU per ml, so 10 units on a U-100 syringe hold 7.5 IU. With 1.5 ml it gives 50 IU per ml and 10 units hold 5 IU. Add the water down the vial wall and swirl, never shake.
Yes. Menotropin sits in WADA class S2.2.1, the testosterone stimulating peptides in males, next to HCG and LH. Only men are covered, and the prohibition holds at all times rather than in competition alone. Without a diagnosed deficiency a therapeutic use exemption is not realistic, so the rule deserves to be treated as absolute.
In women the warnings cover ovarian hyperstimulation, cyst rupture, multiple births and thromboembolism, which is why treatment is supervised by a specialist. In men the more common effects are injection site reactions, fluid retention, acne and mood changes. Because it is a urinary extract, there is a theoretical donor-related infection concern.
You can buy HMG by Generic Peptides online at XSteroids, direct from the brand catalog. Choose the 75 IU menotropin vial on this page, add it to the cart and complete the order with secure checkout. US domestic delivery takes 3 to 6 days and international shipping 12 to 26 days.
Loading...
Your cart is currently empty. Let us assist you in finding the right product